










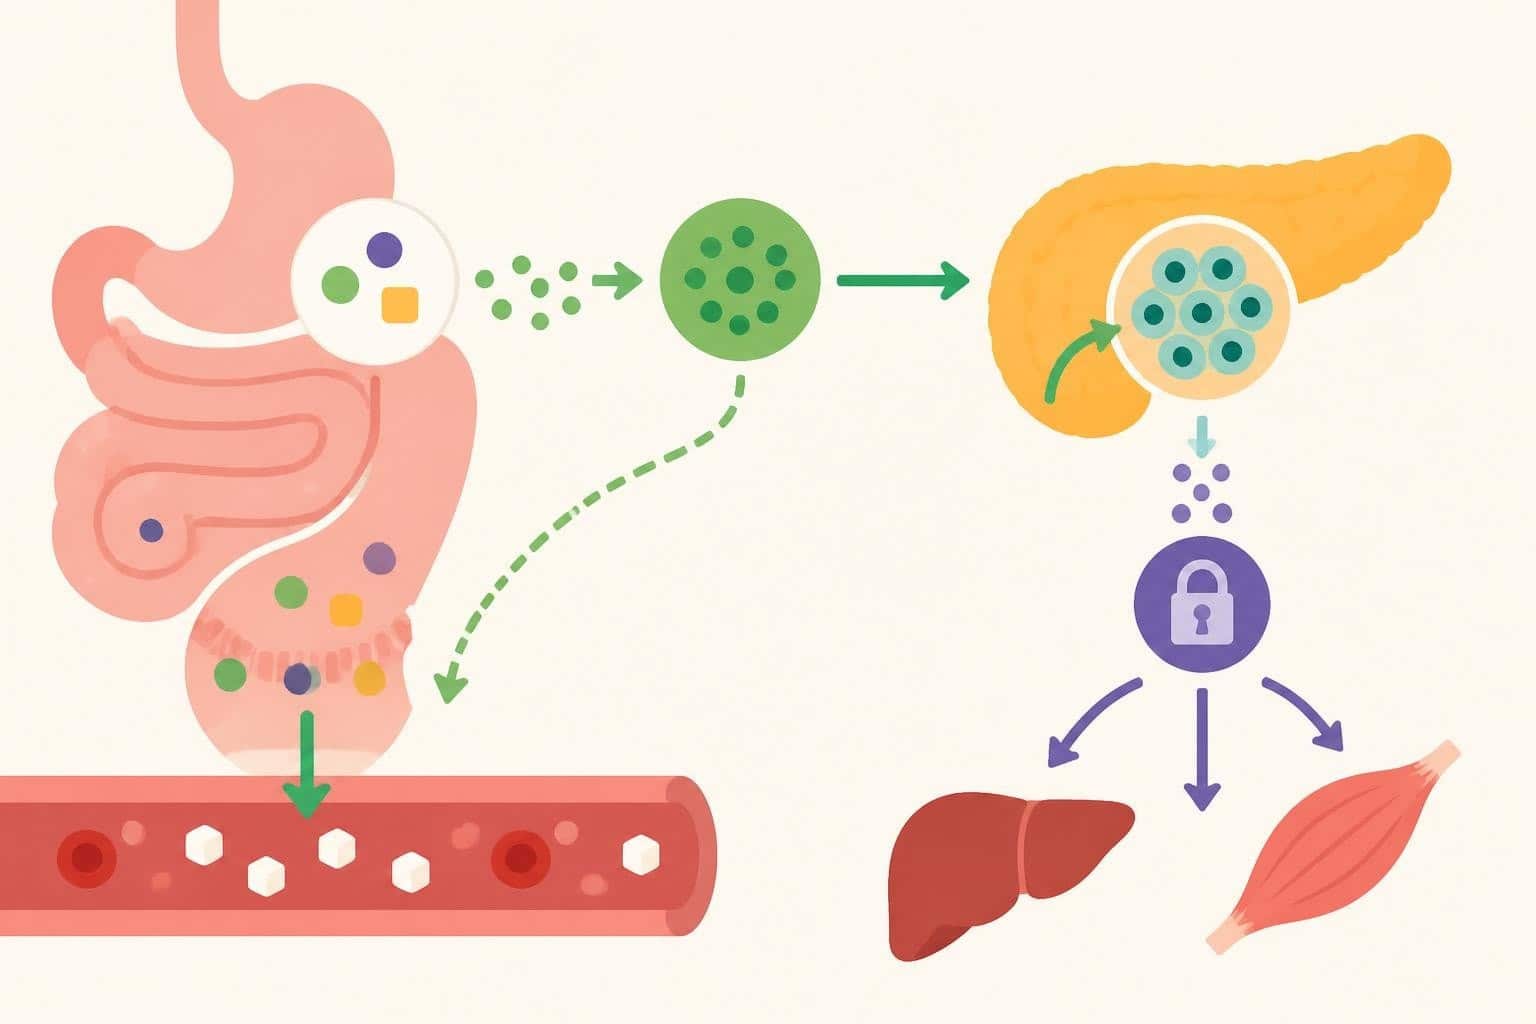
Glucose-dependent insulinotropic polypeptide, commonly known as gip peptide, represents one of the most significant hormones in human metabolism. Originally identified as gastric inhibitory polypeptide before researchers uncovered its true metabolic function, this incretin hormone has become central to understanding how the body manages glucose homeostasis and energy balance. As therapeutic applications expand in 2026, particularly in metabolic disease management, gip peptide continues to reveal new dimensions of its physiological importance beyond its classical role in stimulating insulin secretion.
Understanding GIP Peptide Structure and Secretion
Gip peptide is a 42-amino acid polypeptide hormone synthesized and secreted by K-cells located primarily in the duodenum and proximal jejunum of the small intestine. These specialized enteroendocrine cells respond rapidly to nutrient intake, particularly fats and carbohydrates, triggering the release of gip peptide into the bloodstream within minutes of food consumption.
The molecular structure of gip peptide belongs to the secretin-glucagon hormone family, sharing structural homology with other incretin hormones such as glucagon-like peptide-1 (GLP-1). This structural relationship influences how the peptide binds to its receptor and initiates downstream signaling cascades that affect multiple organ systems.
Molecular Characteristics and Receptor Binding
The bioactive form of gip peptide exhibits a remarkably short half-life in circulation, typically lasting only 2-5 minutes before enzymatic degradation by dipeptidyl peptidase-4 (DPP-4). This rapid turnover necessitates continuous secretion from K-cells during and after meals to maintain physiological effects.
Key structural features include:
- N-terminal region critical for receptor activation
- Specific amino acid sequences that determine binding affinity
- Structural motifs susceptible to DPP-4 cleavage
- Post-translational modifications affecting stability
The GIP receptor (GIPR) is a G protein-coupled receptor expressed predominantly in pancreatic beta cells, but also found in adipocytes, bone tissue, brain, and cardiovascular tissues. This widespread distribution suggests that gip peptide influences multiple physiological processes beyond glucose regulation, as detailed in comprehensive reviews of incretin physiology and GIP’s multifaceted role.
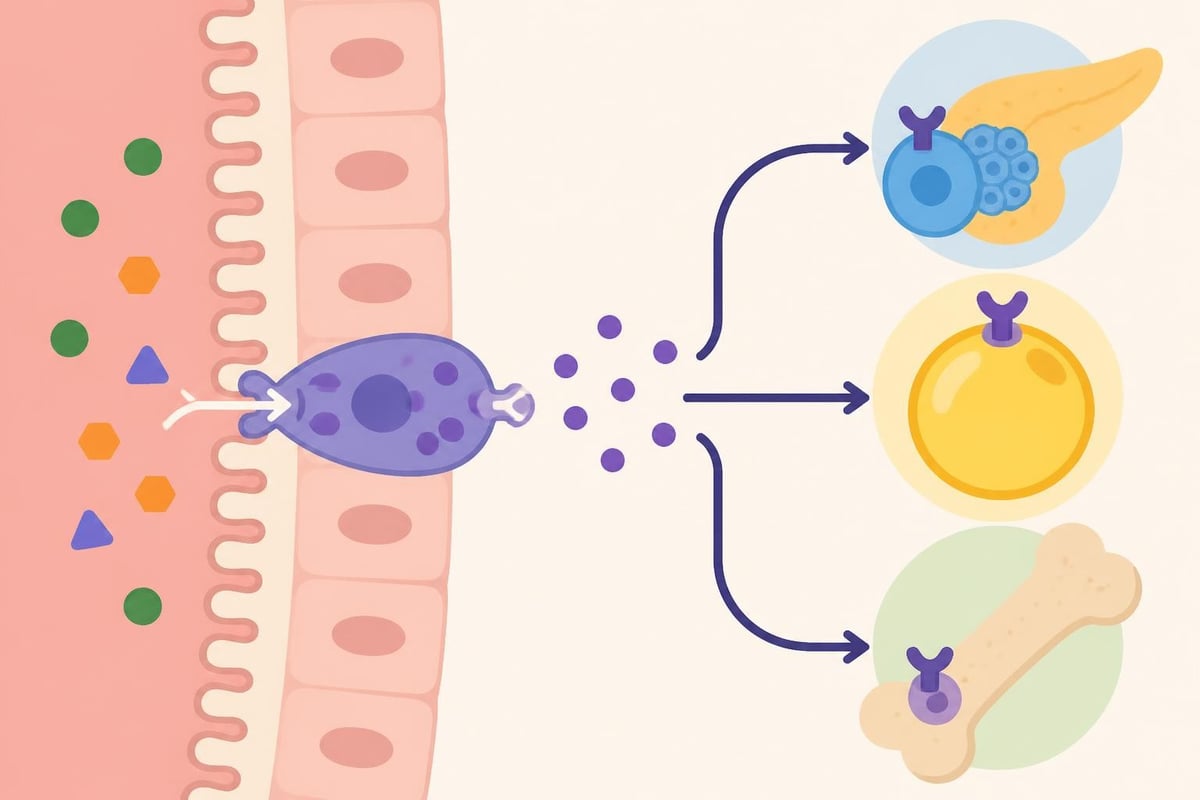
Physiological Functions of GIP Peptide
The incretin effect, in which oral glucose administration produces a greater insulin response than intravenous glucose delivery, owes approximately 60-70% of its magnitude to gip peptide activity. This fundamental observation established gip peptide as a critical component of normal glucose homeostasis and metabolic regulation.
Glucose Metabolism and Insulin Secretion
Gip peptide functions as a glucose-dependent insulinotropic agent, meaning it enhances insulin secretion only when blood glucose levels are elevated. This conditional mechanism provides an inherent safety feature that minimizes hypoglycemia risk compared to therapies that stimulate insulin release regardless of glucose status.
When gip peptide binds to receptors on pancreatic beta cells, it activates adenylyl cyclase, increasing cyclic AMP (cAMP) levels. This second messenger cascade amplifies glucose-stimulated insulin secretion through multiple pathways including calcium influx, protein kinase A activation, and enhanced insulin gene transcription.
Research has demonstrated that GIP’s physiological actions extend well beyond simple insulin secretion, influencing beta cell proliferation, survival, and function under various metabolic conditions.
Lipid Metabolism and Adipocyte Function
Beyond its pancreatic effects, gip peptide exerts significant influence on adipose tissue metabolism. The peptide promotes lipogenesis and fat storage in adipocytes through several mechanisms:
- Enhanced lipoprotein lipase activity
- Increased fatty acid uptake from circulation
- Stimulated triglyceride synthesis
- Reduced lipolysis in the postprandial state
These actions facilitate efficient nutrient partitioning after meals, directing ingested fats toward storage rather than oxidation. While this represents normal physiology in healthy individuals, the role of gip peptide in obesity development has sparked considerable research interest and therapeutic investigation.
| Tissue Target | Primary GIP Action | Metabolic Outcome |
|---|---|---|
| Pancreatic Beta Cells | Insulin secretion enhancement | Improved glucose clearance |
| Adipocytes | Lipogenesis promotion | Increased fat storage |
| Bone Tissue | Osteoblast activity | Enhanced bone formation |
| Central Nervous System | Neuroprotective signaling | Cognitive support |
GIP Peptide in Disease States
Understanding how gip peptide function changes in metabolic disease provides insight into both pathophysiology and therapeutic opportunities. Type 2 diabetes mellitus, obesity, and metabolic syndrome all feature alterations in GIP signaling that contribute to disease progression.
Type 2 Diabetes and Incretin Resistance
Individuals with type 2 diabetes exhibit a phenomenon termed "GIP resistance," characterized by diminished insulinotropic response to gip peptide administration despite normal or elevated GIP levels. This contrasts with preserved GLP-1 responsiveness in many patients, explaining why GLP-1-based therapies initially dominated incretin-based diabetes treatment.
The mechanisms underlying GIP resistance include:
- Downregulation of GIP receptors on beta cells
- Impaired post-receptor signaling cascades
- Beta cell dysfunction reducing secretory capacity
- Chronic hyperglycemia affecting receptor sensitivity
Recent investigations suggest that GIP resistance may be reversible with metabolic improvement, indicating that beta cell function restoration could re-establish normal gip peptide responsiveness.
Obesity and Weight Regulation
The relationship between gip peptide and obesity remains complex and somewhat controversial. Early research suggested that reducing GIP activity might promote weight loss by decreasing lipogenesis and fat storage. However, more recent evidence indicates that GIP and GLP-1 exhibit contrasting cardiometabolic actions that cannot be simply categorized as beneficial or detrimental.

Interestingly, some obesity phenotypes show elevated GIP secretion in response to meals, potentially contributing to excessive fat accumulation. This observation led to therapeutic strategies either blocking GIP action or, paradoxically, using sustained GIP agonism to induce receptor desensitization and reduce lipogenic effects.
Therapeutic Applications and Drug Development
The pharmaceutical industry has leveraged understanding of gip peptide biology to develop novel metabolic therapeutics that represent major advances in diabetes and obesity management. These medications demonstrate how basic incretin research translates into clinical benefit.
Dual and Triple Agonist Therapies
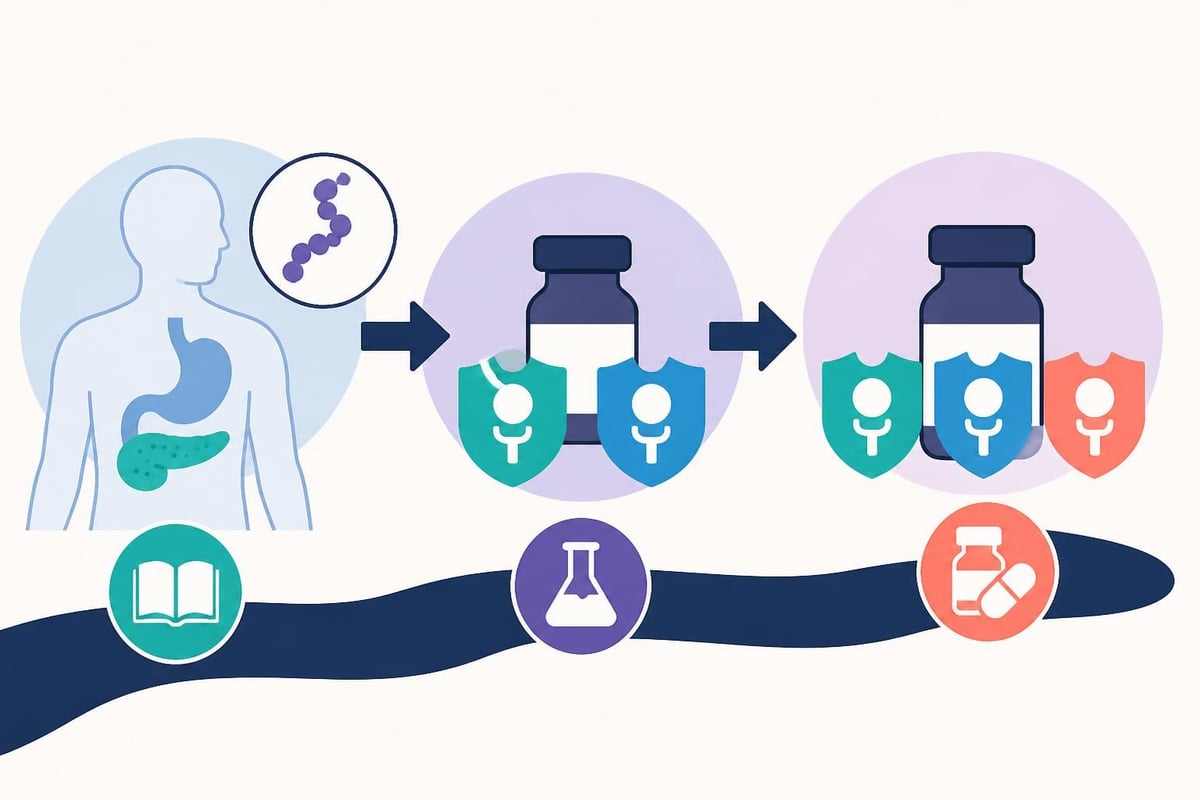
Modern GIP-based therapeutics often combine GIP receptor agonism with activation of other incretin pathways. Tirzepatide, approved for type 2 diabetes and obesity treatment, functions as a dual GIP/GLP-1 receptor agonist, producing superior glycemic control and weight loss compared to GLP-1 agonists alone.
The mechanisms behind enhanced efficacy include:
- Complementary insulin secretion pathways
- Synergistic effects on appetite regulation
- Broader metabolic tissue targeting
- Improved energy expenditure
Emerging triple agonists that activate GIP, GLP-1, and glucagon receptors show even greater promise for weight reduction and metabolic improvement. These medications harness gip peptide signaling alongside other hormonal pathways to create comprehensive metabolic rebalancing.
Researchers continue exploring different GIP analogs and GIP antagonist approaches as therapeutic tools for metabolic disease, recognizing that both agonism and antagonism might offer benefits depending on clinical context and patient phenotype.
Cardiovascular and Bone Health Applications
Beyond metabolic effects, gip peptide influences cardiovascular function and bone metabolism through direct receptor activation in these tissues. Preclinical studies suggest that GIP signaling may promote:
- Endothelial function improvement
- Reduced inflammatory markers
- Enhanced bone formation through osteoblast activation
- Protection against bone resorption
These pleiotropic effects position gip peptide-based therapies as potentially addressing multiple comorbidities common in metabolic disease populations, including cardiovascular disease and osteoporosis.
GIP Peptide Research and Future Directions
Scientific investigation of gip peptide continues to reveal unexpected functions and therapeutic possibilities. The historical evolution of GIP research demonstrates how initial observations about gastric acid inhibition gave way to recognition of its profound metabolic importance.
Neurological and Cognitive Effects
Recent evidence indicates that gip peptide receptors in the central nervous system may influence cognitive function, neuroprotection, and eating behavior. These findings suggest therapeutic potential beyond traditional metabolic applications:
- Memory and learning enhancement
- Neuroprotective effects in neurodegenerative diseases
- Mood regulation pathways
- Appetite and satiety signaling
The blood-brain barrier penetration of native gip peptide remains limited, but modified analogs with improved central nervous system access could unlock novel neurotherapeutic applications.
Personalized Medicine Approaches
Understanding individual variation in GIP responsiveness opens possibilities for personalized metabolic medicine. Genetic polymorphisms in the GIP receptor gene correlate with differences in:
- Beta cell function and diabetes risk
- Body composition and obesity susceptibility
- Bone density and fracture risk
- Treatment response to incretin-based therapies
| Research Area | Current Status | Potential Application |
|---|---|---|
| Neurodegenerative Disease | Preclinical | Alzheimer's and Parkinson's therapy |
| Cardiovascular Protection | Clinical Trials | Heart failure and atherosclerosis |
| Bone Metabolism | Established | Osteoporosis prevention |
| Cancer Metabolism | Early Investigation | Metabolic targeting in tumors |
Pharmacogenomic testing may eventually guide selection of GIP-based versus GLP-1-based therapies based on individual receptor profiles and metabolic phenotypes.
Clinical Considerations for GIP-Based Therapies
Healthcare providers prescribing GIP-containing medications must understand both their benefits and potential considerations. While generally well-tolerated, these therapies require appropriate patient selection and monitoring to optimize outcomes.
Patient Selection and Monitoring
Ideal candidates for GIP-based therapies typically include individuals with type 2 diabetes requiring improved glycemic control or those with obesity seeking significant weight reduction. However, certain patient characteristics influence treatment decisions:
Favorable patient profiles:
- Preserved beta cell function
- Elevated postprandial glucose excursions
- Obesity with metabolic complications
- Inadequate response to GLP-1 monotherapy
Monitoring parameters:
- Hemoglobin A1c and glucose trends
- Body weight and composition changes
- Gastrointestinal tolerance
- Cardiovascular risk markers
The gastrointestinal side effects common with incretin therapies, including nausea and altered bowel habits, generally diminish with continued use as tolerance develops.
Integration with Other Therapies
Gip peptide-based medications integrate effectively into comprehensive metabolic management programs. They complement lifestyle interventions, other diabetes medications, and peptide therapies targeting recovery and metabolic health.
Combination approaches might include:
- Metformin for insulin sensitization
- SGLT2 inhibitors for renal protection
- Lifestyle modification for sustainable results
- Nutritional optimization to support metabolic goals
The synergistic effects of combining GIP agonism with other mechanisms often produce superior outcomes compared to monotherapy approaches.
Molecular Variants and Analog Development
The rapid degradation of native gip peptide by DPP-4 necessitated development of modified analogs with extended half-lives for therapeutic use. These modifications represent sophisticated pharmaceutical chemistry addressing specific biological challenges.
Structural Modifications for Stability
Therapeutic GIP analogs incorporate several design features that enhance stability while preserving or enhancing receptor activation:
- Amino acid substitutions at DPP-4 cleavage sites
- Fatty acid conjugation for albumin binding
- Pegylation to increase molecular size
- Conformational constraints improving receptor selectivity
These modifications extend half-life from minutes to days, enabling once-weekly or even less frequent dosing schedules that improve patient adherence and convenience.
Detailed investigations into GIP receptor binding regions have informed rational design of analogs with optimized pharmacological properties, balancing potency, selectivity, and duration of action.
Biased Agonism and Selective Signaling
Advanced understanding of GIPR signaling reveals that different agonists can preferentially activate specific downstream pathways, a phenomenon called biased agonism. This enables development of gip peptide analogs that:
- Maximize insulin secretion while minimizing lipogenic effects
- Enhance cardiovascular benefits relative to metabolic actions
- Selectively target bone formation without affecting adipose tissue
- Achieve tissue-specific effects through differential receptor coupling
Such selective signaling offers potential for next-generation therapeutics with improved benefit-to-risk profiles tailored to specific clinical indications.
Comparative Incretin Physiology
While gip peptide shares incretin functions with GLP-1, important differences distinguish their physiological roles and therapeutic applications. Understanding these contrasts informs clinical decision-making and drug development strategies.
GIP Versus GLP-1 Actions
Both incretins stimulate glucose-dependent insulin secretion, but their broader metabolic effects diverge significantly. The comprehensive analysis of GIP physiology highlights several key distinctions:
| Feature | GIP Peptide | GLP-1 |
|---|---|---|
| Primary secretion trigger | Fats and carbohydrates | Carbohydrates and proteins |
| Gastric emptying | Minimal effect | Marked slowing |
| Adipocyte effects | Promotes lipogenesis | Neutral or lipolytic |
| Glucagon secretion | Context-dependent | Suppresses |
| Diabetes resistance | Common | Rare |
These differences explain why dual agonists combining both pathways often outperform single-incretin therapies. The complementary actions address multiple aspects of metabolic dysfunction simultaneously.
Glucagon's Relationship with GIP
The glucagon receptor shares structural similarity with GIPR, and some GIP analogs exhibit cross-reactivity. Intentional triple agonism (GIP/GLP-1/glucagon) leverages glucagon's effects on energy expenditure and hepatic glucose production to enhance weight loss and metabolic improvement.
Understanding these receptor relationships enables rational polypharmacology that harnesses synergistic mechanisms while avoiding counterproductive interactions.
Safety Profile and Adverse Effects
Clinical experience with GIP-based therapies has established generally favorable safety profiles, though certain adverse effects require recognition and management. Long-term safety data continue accumulating as these medications see broader use.
Common and Serious Adverse Events
The most frequently reported side effects with gip peptide-containing medications mirror those of other incretin-based therapies:
Common (>10% incidence):
- Nausea and decreased appetite
- Diarrhea or constipation
- Abdominal discomfort
- Injection site reactions
Less common but notable:
- Pancreatitis risk (controversial)
- Gallbladder disease with rapid weight loss
- Hypoglycemia when combined with insulin or sulfonylureas
- Altered thyroid function in susceptible individuals
Most gastrointestinal effects diminish substantially within 4-8 weeks of treatment initiation as physiological adaptation occurs. Gradual dose titration minimizes these tolerance issues.
Long-Term Safety Considerations
Extended observation of patients using GIP-based therapies will clarify their long-term safety profile. Areas of ongoing surveillance include:
- Cardiovascular outcomes in high-risk populations
- Bone density changes with chronic use
- Malignancy risk assessment
- Renal and hepatic function over time
Current evidence suggests cardiovascular benefits rather than risks, and bone effects appear neutral to beneficial, but continued monitoring remains prudent.
Optimizing GIP Peptide Response
Individual response to gip peptide-based therapies varies based on genetic, metabolic, and lifestyle factors. Optimizing therapeutic outcomes requires attention to factors that enhance or diminish GIP effectiveness.
Nutritional Considerations
Dietary composition influences both endogenous GIP secretion and response to exogenous agonists. Strategies to optimize gip peptide effects include:
- Moderate fat intake to stimulate physiological GIP release
- Balanced macronutrient distribution supporting stable glucose
- Adequate protein for satiety and muscle preservation
- Fiber-rich foods modulating nutrient absorption
Working with qualified nutrition professionals helps patients align dietary patterns with their therapeutic regimen for maximum benefit.
Lifestyle Integration
Exercise and sleep quality significantly affect metabolic hormone sensitivity, including gip peptide responsiveness. Regular physical activity enhances insulin sensitivity, potentially restoring GIP effectiveness in insulin-resistant states.
Quality sleep supports normal incretin physiology through multiple mechanisms including inflammatory modulation, appetite hormone regulation, and glucose metabolism optimization. Patients achieving 7-9 hours of consistent sleep typically demonstrate better outcomes with metabolic therapies.
Comprehensive lifestyle approaches that address nutrition, movement, sleep, and stress create the optimal foundation for gip peptide-based interventions to achieve their full potential. Those seeking additional support for metabolic health and recovery may benefit from exploring premium quality peptides designed for these purposes.
Gip peptide has evolved from a gastric hormone curiosity to a central player in metabolic therapeutics, with clinical applications expanding rapidly as our understanding deepens. Its unique combination of insulin secretion enhancement, lipid metabolism regulation, and broader tissue effects positions GIP-based therapies at the forefront of diabetes and obesity treatment in 2026. For individuals seeking to optimize their metabolic health through evidence-based peptide therapies supported by rigorous quality standards, Soma Peptide offers premium formulations designed to support weight management, recovery, and overall wellness goals.